fredag den 31. oktober 2014

Are the new hospitals in Denmark really really super?

The press has named the new hospitals in Denmark to super hospitals. It is a very ambitious word - super – to be using and it rests heavily on everyone's shoulders to deliver on these high expectations. However, is it actually super hospitals we are building? Let us first define what the word actually means super.

According http://www.denstoredanske.dk/ means SUPER following:

super, (lat. 'above'), Latin and international prefix denoting location, extent or amount, see. superpower, which is a particularly powerful superpower; is also used with reinforcing intention in everyday terms like super good.

We are dealing with a concept that can be compared to top-notch and great (maybe even unique according Gyldendals dictionary. Super has a reinforcing effect and it increases a given value of the word it attaches to. As in the example above, then super good, is better than just good. Let us take two examples

The first is from space:

nova (from Lat. (stella) nova 'new (star)', feminine form of novus 'new'), star whose brightness in a matter of days, from a thousand to a million times greater. During months, for slow novas years, the brightness decreases gradually to a normal for the star.

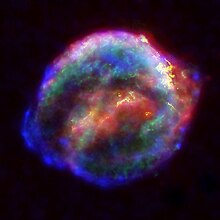
A supernova is a stellar explosion that briefly outshines an entire galaxy, radiating as much energy as the Sun or any ordinary star is expected to emit over its entire life span, before fading from view over several weeks or months.


This first is a slow increase in intensity and brightness to eventually return to its original strength. A supernova is a doomsday explosion in a short time that can outshine an entire galaxy. See that is truly super.

The second example is the word man and superman. Superman is characterized by the fact that he has (super) powers, x-ray vision, is invulnerable, can manipulate time and has a super moral that helps him, he fights evil and saves the world again and again. Superman is not any man - no, he is a superman because of his superb qualities.

So a super hospital must be something much more than just a hospital. But as with Superman and his forces, sight, etc., what characterizes a super hospital and are we actually going to build them or are we building minimally improved hospitals that does not deserve the title of super. I can often be in doubt. Especially because the press in Denmark has focused on the lack of founds, the decrease in the amount of beds and overall quality in all the hospital construction projects. I guess the politicians are right, when they say that you cannot judge the future hospitals superpowers by the amount of beds. The clinical area will change much within the next 8 years, so to talk about the design, architecture and the correlation to the future healthcare delivery is just not possible.

But then it is also obvious that the argument goes both ways – you do not know the healthcare sector of the future – and therefore you do not know if your future hospital will be super!

The only real fact is, that the hospital will be new, shining, white, single patient rooms etc. But if super is new way of delivering healthcare, new ways technologies that supports the healthcare of tomorrow – you don’t know. Super in that equation is new as in a new building – the rest is pure speculation.

So what is a super hospital is the million dollar question that everybody assumes they know – but none articulate it in detail. The. Expert Committee has identified areas they believe characterizes a super hospital. You must increase the hospital operation efficiency by 8 per cent , build single man patient rooms, increase productivity and convert treatment towards more day surgery, thereby allowing the closure of almost 20 per cent beds. Very practical but probably not the full picture of a super hospital

New OUH's vision is trying to define the super hospital, but if you are going a step deeper: what characterizes it in detail - no one knows - but everybody says it - super!

It would be interesting, now that politicians are the fathers of the super hospitals', to hear their views on what is a super hospital for them? And also what is it for the patients, the employees and of course the general Dane – we are paying for the party through taxes and we expect a super hospital. I guess we all fail if super is not defined.  It is difficult – maybe it is because it is not super at all.

What is a super hospital for you?

onsdag den 8. oktober 2014

Leadership mindsets for IT success

I have recently started teaching University students in IT, Communication and Organization. Basically it is a subject regarding basis IT skills (What is cloud computing, how is the internet designed etc) and secondly it’s about strategy and aligning IT with business objectives. As I have previously mentioned in this blog I find the subject of IT and business fascinating, and I hope to at least empower my students with the knowledge about how it can be done and how hard it actually are to achieve.

Anyway, during my research for the class. I came by a very interesting and accessible little piece regarding the leadership mindsets in business. The article is written by Professor Donald Marchand and Professor Joe Peppard and was released in The European Business Review in March-April 2014 issue.

What I like about the article is, that it focuses the main points and arguments in a short form and in the end; it points the reader to the future by some practical advice.

The authors main point in the article is basically that with different mindsets on IT and information within the business, the role of IT will change: "…these differences in mindsets and thus perceived roles and responsibilities of senior managers and CIOs, the implications for how information recourses, IT, and knowledge are managed in the company will differ.. dramatically."

So the mindset of senior management and the CIO will affect how the company will use and regard IT investments. No new knowledge in that. However, the article suggest a Matrix where the business manager roles on on Axis and the CIO on the other.
http://www.europeanbusinessreview.com/?p=302

An excellent matrix, that gives the necessary input to a discussion on how we regard IT today and where would we like to be. A strategic talk about IT and business.

In the end, the authors suggest two key questions that should be explored during the strategic discussions senior management and IT have. They are as follows:

Where are your group or business unit management teams and CIOs today in terms of mindsets, behavior, and shared language?

Where should your business unit management teams and CIO be in the future related to the strategic management of information, IT and knowledge resources.

I can only recommend the small 4 page article to all management teams – both business and IT – It’s a great start for further elaboration and discussion on how will we regard and ultimatly use IT in our business to gain for example a competitive advantage.

onsdag den 27. august 2014

The planning of IT – is it a necessary evil ?

What if you are in charge of a centralised IT department with infrastructure architects, solution architects, business consultants, account managers etc. And lets say the company is huge and has large departments all over the world. Again lets imagine that the departments are in charge of implementing and administration of the It systems for the entire organisation. So they have, so to speak, divided the systems and projects among themselves leaving the centralised IT department with architectural consulting and Infrastructure as their only areas of responsibility. To govern the IT they have established a kind of Architecture board, where decisions of a strategic level are made as well of decisions of how and which projects to proceed and fund. An important board that if respected and used have the ability to align the decentralised organisation in and around a common business strategy.

I guess with the above organisation,  IT is closer to the business it is supposed to support, it might get the process of funding to run more smooth, because the local management knows exactly where it hurts. It is very agile and can react to imminent issues that may arise as small or medium business can do. The problem, or positive people would say challenges, are of course, to align all the IT initiatives, IT management and operations, IT projects and the overall IT planning process, of the organization as a whole.

When power and decision making are decentralised people tend to decide and use that power. Often not for the greater good of the whole organisation and not for the long term planning – actions are often isolated decisions based on local knowledge, local challenges and therefore short term IT planning.

So no system or organisation is perfect – but maybe we have a solution where we can have both local knowledge and business integration at the same time as long term strategic IT planning.

It is called Enterprise architecture – and it fucking rocks if it is implemented and respected by all the participants in the organization. The video below quickly explains the concept of enterprise architecture way better than I can, so please take four minutes to watch it.


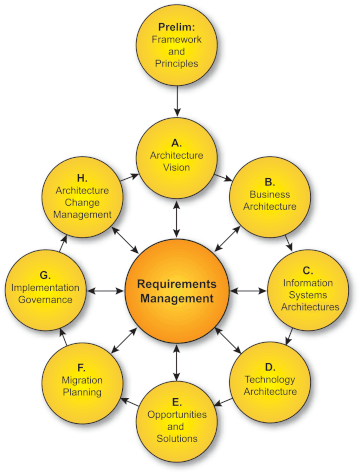
I am certified in TOGAF 9.1 Enterprise Architecture and that is just one out of a handful methodologies regarding enterprise architecture.  The real issue with the TOGAF framework or more precise the Architecture development method (ADM)
The open Group (opengroup.org)
is to gain enough speed in the administrative process, that implementing EA will not result in a standstill of the IT within the business.  If that happens, the business units will just circumvent the EA processes and acquire the IT themselves. The more the individual departments operate on their own – the more short termed and individual are the IT planning – but then again it is closer to the business needs. On the other hand the more centralised IT is planned, the more administrative and bureaucratic everything can tend to be and then it will of course be further away from the eminent business challenges.

I guess I don’t have the answer except that short and long term planning is necessary. The TOGAF EA is a great way to handle it – It just need all to respect the processes established and it needs to be tailored to the organisation it is supposed to support – otherwise the resources are lost and we might even be further away than when we started to plan for IT in the first place.

By the way - good people will leave in all the parts of the organization if you do not respect the craft of doing IT properly. Especially the enterprise architects will not tolerate that business and IT is done with no planning and with a little or no respect to strategies, business needs and the processes that have proven best. TOGAF calls that capability based planning - how the overall EA capability of the organization is established and maintained -  don't ever ignore that in your organisation either.

onsdag den 20. august 2014

There is no such thing as a pilot in the healthcare sector

I often wonder why IT projects within the healthcare sector, always takes a lot of time or end up so big, that the project management cannot handle them and the project schedule is delayed.

Often in IT projects there are a clear understanding of the business case, the goals and purpose of the system. But people never the less does not talk about what a pilot is for and why they have chosen that particular method and for example not a lab test instead. In healthcare there are no such things as a pilot, because we need to focus on patient security and a high quality of the delivered treatment. Pilots with less functionality or even simulated data flows, do not go well within that paradigm.

In my time in IT management in a big university hospital I heard more than the opposite doctors and nurses argue, that a pilot project would be ok, but not until that integration or that functionality is implemented as well. If project management give in, the project is growing and the pilot will not start until the entire system is in place, and that can take a lot of time. Low hanging fruit slowly ascends into the three tops so to speak, and are harder to reach.

Projects in the healthcare sector can be illustrated with one of my personal favourite Gifs. Everything is lined up, the field is well described and marked, the goal is clear and in sight and you has even implemented some organizational and functional routines to help the system into implementation. But quick the project gets to big and crashes half way towards a milestone.
 
I guess one way to solve the above paradox is to really understand and communicate the purpose of the pilot and not let the project grow out of its initial scope. Furthermore, always make it clear, that the system after ending the pilot might get shut down, so you will not make severe adjustments for a lot of money on a system that might not be implemented fully within the organization.

So my I guess my point is, that be careful with your health IT projects, get it aligned exactly with the business needs and don’t overdue the functionality. Keep the fruit low and don’t let perfect be the enemy of good.

torsdag den 19. juni 2014

The power of simplicity - a way of looking at Requirements

Based on the clinical concepts of the New University Hospital and decisions about design and architecture we can identify a range of functional requirements that describe future processes, working methods etc on New University Hospital. Decisions for example that we build single person patient rooms single rooms or the establishment of cluster pharmacies will also require a wide range of requirements for future solutions.
From these functional requirements we then can identify a number of IT requirements that will make us able to solve or meet the functional requirements. These IT requirements can be assembled in IT solutions that solve one or usually more functional requirements. In other words, it reflects the clinical concepts and architecture and design requirements for future hospital - IT solutions ensure that these can be realized.

The following is an example where the kitchen and food logistics concept and the choice of making local floor kitchens around the hospital will cause the food to be transported from the central kitchen out to the floor kitchens. Here it is prepared and served on trays to patients. The Central kitchen staff therefore requires that they can monitor the food temperature from leaving the central kitchen to arrival in the floor kitchen. This is referred to as they want to monitor if the "temperature chain is broken." This can be solved in many ways, and one of them is to install censors in the crates which food is stored in. Data on temperature must be collected in an IT system, and to be given an alarm if the temperature rises to an agreed level and therefore the temperature chain is broken. Functional requirements from the central kitchen about securing healthy food that are always cold ends with an IT solution or an expansion of existing solution, so it is possible to continuously monitor the temperature of the food and give a warning if the temperature rises above a defined level.

The method is rather easy to understand, to communicate and it ensures that we always focuses on the business requirements and not start with IT. I guess a simple, understandable and effective method is always preferred in a busy schedule. It works for us at least.


tirsdag den 10. juni 2014

Benefit Management may save us all!

I just read a thesis from the University of Aarhus, about harvesting value in IT projects. The students named the area as Benefit Management (profit realization), and is a highly relevant and general area that many organizations should prioritize. Particularly in the health sector.!

I've often wondered that in such a research-heavy and evidence-based system such as health care sector, how can you introduce New Technology, new processes around technology and new skills among staff, without knowing the evidence or just the effect on productivity or perhaps quality.?

Currently there are deployed  IT in the Danish health like in a pace not seen before. In Region Southern Denmark the regional project portfolio consist of more than 50 large and small projects, so spending millions and billions on a national level - and what do we get out of it? Well to put it bluntly we often don’t know!

Benefits management is defined in the book "Benefits Management – How to increase the business value of your IT projects" written by Ward, J. & Daniel, E. 2012 as:

“The process of organizing and managing such that the potential benefits arising from the use of IT are actually realized” (page 8)

Benefits Management is all about identifying and harvesting the value that a given project has the potential to realize. Currently projects are not initiated in Region of Southern Denmark without having drawn up a business case. But how will the projects be prioritized towards each other? And do we work adequately with identifying the value a given project may realize. Maybe – but probably not.

But when the system, technology or equipment is implemented, how is it ensured that the gains that were identified in the business case is realized. ? There may have been a tendency not to make this impact assessment, evaluation, or otherwise measure whether what you thought you got out of a project. Traditionally, the value collected are invisible deep within the operation of the organization. The point is that we often do not know what the value is and therefore we cannot harvest it.


I guess benefit management has two major objectives. One is on a macro project management level to harvest the value on a organizational level. It could be to increase the effectiveness with 2 pct. or to reduce adverse events. The other is on a local level, where the individual ward or department can identify their special benefits from the implementation and then try to work towards those when implementing the system. Done right it may help on the projects implementation success rate on a local scale, because the receiving users take responsibility on the implementation and the goals/benefits regarding it.

In my organization we have used the Himss IT value suite. In short it is a framework to identify the following:

•    How do we know Health IT works?
•    How does Health IT improve patient care?
•    Can others duplicate the type of value others have achieved?

The framework is suitable both on the managerial/organisational level but also on the local level, where a discussion with the headline “what is a successful implementation in our ward” the main issue.

Benefit management is and must be our focus otherwise we invest, implement, learn and reinvest in the dark. To know the impact is crucial also because only then are we able to share our experience and help others in their efforts.

It took two very talented, hard-working and well-prepared students to get my eyes to the problem again. (I gave them the grade 12 for the rest). They introduced me to the field on an academic and structured way. The road is paved with endless amounts of benefits and value of digitization - we all have an obligation to pursue these unyielding, and the courage to harvest them  in a proper and professional manner.

Ward and Daniel is a great book by the way – and I highly recommend it.


søndag den 1. juni 2014

A full automated, double loop medication process in action – awesome expierence

In our project there is I clear line between the choice of less beds,  a fixed amount of m2 and an 8 pct efficiency increase, to new solutions that will help the hospital to operate in the new environment. The best is of course a solution, that will meet those requirements and increase the overall quality of the care delivered. IT has a tremendous role in that equation. So instead of talking about an increase in beds or m2, the discourse is and must be about new solutions because the constrains are fixed.

Last week I was in France – Annecy to visit a hospital that was build a couple of years ago. On the IT side the wards, patient rooms, EHR, RIS/PAS etc we were quite up to speed. They did not have anything revolutionary installed, and they to had a lot of patient terminals that no clinician used. But then I realised they did not have any big medicine rooms on the actual ward only a small area with acute medicine. So that intrigued me, because New OUH will be build that way.

We were then allowed to visit their pharmacy and there I got a huge surprise. Everything was automated, every drug was tracked and medicine was delivered to the ward automatically based on the data the doctor ordered in the EHR. For the first time a saw the whole process automated and it was a great success.

An Italian firm had delivered the robots (I guess they are better on healthcare robots than on trains) and the system seems to run smoothly.

Pill pick robot and unit dosed medicine
So
  1. Robot that cuts medicine from the blister packs into one unit packets
  2. Robot that counts the units to ensure they are all there
  3. Robot that packs the units in separate bags withs barcodes and RFID
  4. Robot that stores the units
  5. EHR registers medicine prescribed and send data to pill pick robot
  6. Pill Pick robot then picks the units and packs them for the individual patient and bind them together
  7. The medicine is then shipped to the ward by a tube system


The above is not a futuristic vision – it is real and in operation in France. It will save m2, increase efficiency and tremendously decrease the amount of adverse events due to errors in the medication process. What’s there not to like for a future digital, “small” and efficient hospital.?